
 See Our Latest Article on HelloNation

Pregnancy can bring low-back pain, pelvic discomfort, hip stiffness, and changes in posture. For some people, chiropractic adjustment may be a reasonable part of symptom management—but it is not automatically appropriate for every pregnancy or every type of pain.
The safest answer is: some pregnant patients can be adjusted safely when the technique is adapted for pregnancy and the patient’s maternity-care team is aware of the treatment. Research on spinal manipulation during pregnancy remains limited, so safety depends on health history, pregnancy status, symptoms, positioning, and practitioner training. Serious complications have been reported rarely, but the available evidence is not strong enough to treat adjustments as risk-free. ([nccih.nih.gov](https://www.nccih.nih.gov/health/spinal-manipulation-what-you-need-to-know?utm_source=openai))
Is a chiropractic adjustment safe during pregnancy?
For a healthy pregnancy without complications, gentle, pregnancy-adapted manual care is generally considered a possible option for musculoskeletal discomfort. The treatment should not involve forceful positioning, pressure over the abdomen, or techniques that ignore changes in balance, ligaments, circulation, and joint stability.
Pregnancy hormones can make ligaments more flexible. As the abdomen grows, the center of gravity shifts and the muscles of the back, hips, and pelvis work differently. These changes may contribute to discomfort, but they also mean that techniques used before pregnancy may need to be modified.
The National Center for Complementary and Integrative Health reports that serious adverse events from spinal manipulation during pregnancy appear to be very rare, while also emphasizing that rigorous research is limited. That combination supports a cautious, individualized approach rather than a blanket assurance. ([nccih.nih.gov](https://www.nccih.nih.gov/health/spinal-manipulation-what-you-need-to-know?utm_source=openai))
What should happen before an adjustment?
A pregnancy-related adjustment should begin with a health-history review, not simply a request to “work on” a painful area. Relevant details include:
- How far along the pregnancy is
- Whether the pregnancy is considered high risk
- Prior miscarriages, preterm labor, or pregnancy complications
- Placental or bleeding concerns
- High blood pressure or other medical conditions
- Recent falls, accidents, or new injuries
- Numbness, weakness, fever, or unexplained weight loss
- Current medications and restrictions from the obstetric care team
The obstetrician, midwife, or other maternity-care clinician should be informed, especially if the patient has complications or has been told to limit activity. The American College of Obstetricians and Gynecologists identifies obstetric clinicians and other qualified medical professionals as resources for evaluating pregnancy-related back pain. ([acog.org](https://www.acog.org/womens-health/faqs/back-pain-during-pregnancy?utm_source=openai))
This communication is especially useful when pain is new, severe, rapidly worsening, or not clearly related to posture or movement.
How is prenatal care different from a standard adjustment?
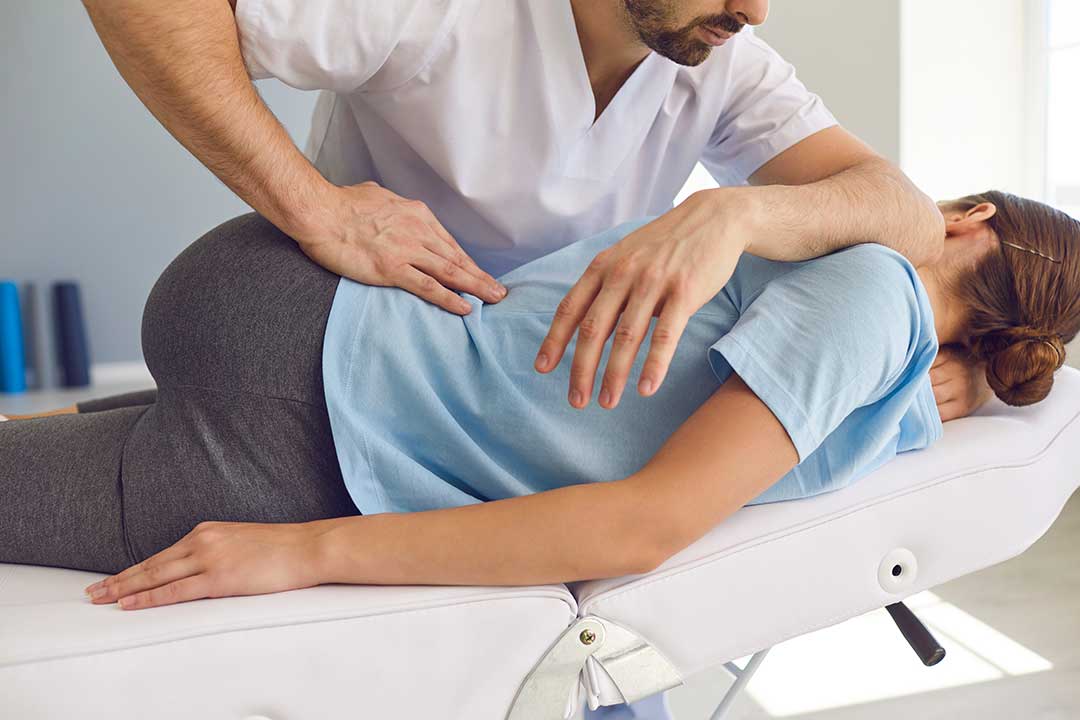
Positioning is one of the main differences. A pregnant patient may be treated on the side with supportive cushions, or in another position that avoids abdominal pressure and prolonged discomfort. Lying flat on the back for an extended period may be uncomfortable later in pregnancy and can cause lightheadedness in some people.
A pregnancy-appropriate session may involve:
- Gentle spinal or pelvic mobilization
- Soft-tissue work
- Guidance on movement, posture, and sleep positions
- Exercises for strength, mobility, and body mechanics
- Supportive positioning using pillows or specialized equipment
A practitioner should explain what will be done, ask whether any position causes dizziness or pain, and stop if symptoms change unexpectedly. High-velocity or forceful techniques are not appropriate simply because they were used before pregnancy. Treatment should be adjusted as the pregnancy progresses.
Can an adjustment help pregnancy-related back or pelvic pain?
It may help some types of mechanical pain, particularly discomfort associated with posture, restricted movement, or irritation of muscles and joints. However, an adjustment does not treat every cause of pain during pregnancy, and evidence about its effectiveness is not conclusive.
ACOG notes that back pain is common during pregnancy and discusses measures such as posture changes, supportive devices, exercise, and other conservative strategies. Physical activity is generally considered safe and desirable during pregnancy when there are no medical or obstetric contraindications. ([acog.org](https://www.acog.org/womens-health/faqs/back-pain-during-pregnancy?utm_source=openai))
For many residents in Babylon, seasonal routines can influence symptoms. Cold weather, slippery sidewalks, snow or ice, and spending more time sitting indoors may increase stiffness or the risk of a minor strain. Those factors can contribute to ordinary musculoskeletal discomfort, but they should not be assumed to explain pain that is severe, sudden, or accompanied by other symptoms.
When should someone avoid an adjustment or seek medical advice first?
An adjustment should be postponed until the patient receives medical guidance when there is a pregnancy complication, unexplained bleeding, suspected labor, or a significant medical condition. Urgent medical evaluation may be needed for symptoms such as:
- Vaginal bleeding or leaking fluid
- Regular contractions or severe abdominal cramping
- Sudden severe back pain
- Fever or feeling acutely ill
- Loss of bladder or bowel control
- New leg weakness or widespread numbness
- Severe headache, vision changes, chest pain, or shortness of breath
- One-sided leg swelling or significant calf pain
- Noticeably reduced fetal movement later in pregnancy
These symptoms are not routine signs of a joint problem. Trying to manage them with an adjustment could delay needed maternity care.
Is the “pop” dangerous for the baby?
The sound sometimes heard during an adjustment is usually related to movement of gas within a joint, not bones cracking. The sound itself does not indicate that the baby was affected. However, the absence of a loud sound does not determine whether treatment was appropriate, and a loud sound does not prove that an adjustment was beneficial.
The more relevant safety questions are whether the technique was medically appropriate, whether the body was positioned safely, whether excessive force was used, and whether warning symptoms were ignored.
What questions should a pregnant patient ask?
Before treatment, practical questions can clarify whether the approach is appropriate:
- Have you treated pregnant patients at this stage of pregnancy?
- How will positioning be modified?
- Which techniques will be avoided?
- What symptoms would make you stop treatment?
- Do you need information from the maternity-care clinician?
- What non-adjustment options may help, such as exercise or mobility work?
A cautious answer is preferable to a promise that treatment is universally safe. Pregnancy changes quickly, and a technique that felt comfortable earlier may not be suitable several weeks later.
For most uncomplicated pregnancies, gentle, individualized care may be considered for musculoskeletal discomfort when coordinated with maternity care. The decision should be based on the person’s health history and symptoms—not solely on the fact that an adjustment helped before pregnancy.
